
Six months in, Congo's Ebola outbreak is 'out of control' and not slowing
Half a year into Congo's outbreak and it is still being described as out of control - here is why a stalled response in a cobalt-rich country is a business problem, not just a humanitarian one.

Six months into Congo's Ebola outbreak, the response is still being described as "out of control" and shows no sign of slowing, according to Foreign Policy. For decision-makers, an uncontrolled outbreak in a country central to global cobalt and copper supply is a logistics, workforce and reputational risk that surfaces long before it reaches the financial statements.
Six months in, and Congo's Ebola outbreak is still being described in the bluntest available terms: out of control. As Foreign Policy puts it, there is no sign of the outbreak slowing down. That is the entire update in two sentences, and it is a worse story than it sounds. Six months is historically the marker at which an outbreak response either bends the epidemic curve or stops pretending it will. Right now the response is not racing the virus. It is trailing it.
In outbreak terms, "out of control" is not a mood. It typically means transmission chains the response can no longer fully trace, new infections appearing outside known contact lists, and responders reacting to cases rather than anticipating them. When that happens, every missed case becomes its own cluster, and every cluster widens the geography the response has to cover. Ebola makes that arithmetic especially cruel: the virus spreads through direct contact with the bodily fluids of a symptomatic patient, which means the people at highest risk are the ones doing the caring, including family members, nurses, traditional healers and burial teams. Every untraced case is therefore also a staffing risk to the response itself.
For context, Ebola was first identified in 1976 in what is now the Democratic Republic of the Congo, near the Ebola River, and Congo has recorded more outbreaks than any other country. The reference case remains the 2014-2016 West Africa epidemic, which killed more than 11,000 people and cost Guinea, Liberia and Sierra Leone billions in lost output before it was stopped. The lesson the world drew from that episode is that outbreak response is a logistics and trust problem as much as a medical one. The modern playbook typically rests on three legs: finding and isolating cases, tracing and monitoring contacts, and ring vaccination, in which the contacts of confirmed cases and their contacts are immunized to build a firewall of immunity around each infection. Vaccines and treatments have improved substantially since 2014. None of them work if responders cannot reach the people who need them.
Congo is vast, and the parts of it where Ebola has historically burned are frequently the parts with the weakest roads, the thinnest health staffing and the least reliable security. Historically, outbreaks in the east have unfolded in a region shaped by decades of armed conflict, displacement and a deep local suspicion of outsiders, a suspicion that is not irrational given the history of extraction and violence there. Community mistrust is not a public relations problem in this context. It is an epidemiological one. If families hide the sick or bury the dead in secret, the virus gets a head start that no vaccine can claw back.
Money is the second constraint, and it moves on its own rhythm. Outbreak response runs on donor funding, and that funding historically arrives in spikes: fast at the start of a crisis, slower as global attention drifts. Six months in is precisely when the spike typically flattens. The World Health Organization's emergency contingency fund has historically been sized for days and weeks of response rather than months, which is why each major outbreak tends to trigger a fresh emergency appeal. For executives, that pattern matters well beyond humanitarian concern. Global health security is a public good that is chronically underfunded between crises and generously funded only after them, and the gap between those two states is where outbreaks grow.
There is a commercial layer here that rarely makes the headline. For context, the Democratic Republic of the Congo is the world's dominant source of cobalt, a critical input for electric vehicle batteries, and a major copper producer. Historically, outbreaks in the region have disrupted movement across borders, forced screening at airports and crossings, and pushed multinationals to reassess travel policies, staffing rotations and duty-of-care obligations for local workforces. Those are not hypothetical concerns for any company with assets, suppliers or employees in the region. The second-order effects usually show up in logistics and workforce planning long before they show up in earnings.
So what should a board or an operating team actually watch? Four things, all publicly observable. First, whether the outbreak is escalated to a Public Health Emergency of International Concern, the WHO's highest alarm, which historically unlocks both money and political attention. Second, whether cases cross into neighboring countries, which turns a national response into a regional one. Third, whether the funding gap closes before the response loses the contact-tracing race, because tracing is the one intervention that cannot be backfilled later. Fourth, whether vaccine and treatment supply holds up under sustained demand.
The uncomfortable truth about Ebola is that it is cheap to stop early and extraordinarily expensive to stop late. Six months into an outbreak still described as out of control is the definition of late. The medical tools are better than they have ever been. The binding constraints are access, trust and the willingness to fund a response before the crisis makes the news rather than after. For anyone tracking global risk, the question is no longer whether Congo's outbreak is a health emergency. It is whether the rest of the world is prepared to treat it like one.
This story's Key Insights and Take-aways are locked.
Create a free account to unlock Executive Actions for one credit.
Register to UnlockAlways free for Executives Club members. Join the Club
More in Politics

Fifth Circuit Kills Pregnant Workers' Law Over Pandemic Proxy Votes
A procedural ruling, not a policy one, has blocked a federal pregnancy-accommodation law and put every pandemic-era statute in the crosshairs ahead of an expected Supreme Court appeal.
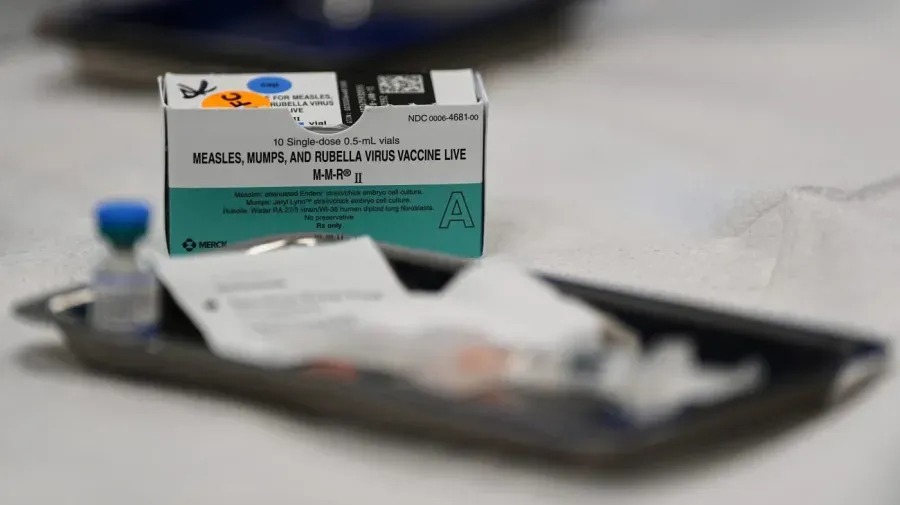
Measles kills a Virginia child under 5, the state's first death of 2026
Virginia's health department confirmed the death but withheld the child's vaccination status, leaving schools, clinics and employers to plan around the one detail that would explain the most.

Former Brazilian President Bolsonaro Hospitalized with Intestinal Obstruction
The health status of the former far-right leader raises immediate questions about political stability and the trajectory of Brazil's conservative movement.